






Trauma is a root cause behind many kinds of distress. For example, a significant share of cases of depression and anxiety can be traced back to trauma. Understanding trauma is essential for resolving persistent problems. Under medical supervision, a Certified Public Psychologist summarizes—in clear terms—what trauma (including developmental trauma) is, and what PTSD / Complex PTSD are. Please read on.
<Created: 2025.9.8 / Last Updated: 2025.9.26>
* If you wish to reprint or otherwise reuse content from this site, please credit the site name as the source or include a link back to this page.
 |
Author of this articleIchitaro Miki — Certified Public Psychologist Osaka University (BA); Osaka University Graduate School (MA) Over 20 years in psychological clinical practice. Specializes in trauma and attachment difficulties that underlie a wide range of problems and “ikizurasa” (chronic distress). Author of Developmental Trauma: The Real Cause of “Ikizurasa” and other books (approx. 40,000 copies in total), appearances on TV programs, clinical supervision for dramas, and numerous features in web media and magazines. |
|---|
Medical supervision for this articleDr. Yoshio Iijima (Psychosomatic Medicine, etc.) A psychosomatic physician who is also a licensed clinical psychologist, Kampo (traditional Japanese) physician, and general practitioner—well versed across disciplines. Specializes particularly in functional somatic symptoms and autonomic nervous system dysregulation. Click here for full profile |
<Editorial Policy>
・Written by a Certified Public Psychologist based on years of clinical experience and client narratives (especially from attachment- and trauma-informed perspectives). Provides explanations and key takeaways.
・References authoritative books and objective data to the best of our knowledge.
・Strives to incorporate the latest findings whenever possible.
・This article has been translated from the original Japanese using AI. Therefore, it may contain unnatural translations, particularly for specialized terms.
Contents
・What is trauma?
・What is developmental trauma?
・What is Developmental Trauma Disorder?
・What is PTSD?
・Diagnostic criteria for PTSD
・What is Complex PTSD?
・Diagnostic criteria for Complex PTSD
・What experiences cause trauma?
・Main symptoms caused by trauma
・Healing and overcoming trauma
→ For related articles on trauma, please see below.
▶ “PTSD/Trauma, Stress, and Mental Care in Disasters (earthquakes, typhoons, accidents, etc.)”
▶ “Overcoming and Healing Trauma (Developmental Trauma), PTSD, and Complex PTSD”
What is trauma?
Trauma has traditionally been understood through the metaphor of a “psychological wound.” It was often associated with the impact of extraordinary events such as war, natural disasters, and serious accidents. In recent years, however, the understanding and definition of trauma have been evolving rapidly. Trauma can result not only from severe stress, but also from prolonged and repeated everyday stress in the home, at school, or in the workplace. Its effects can extend beyond the brain and nervous system to the endocrine and immune systems, as well as to cognition, emotions, one’s sense of self, and interpersonal relationships.
In other words, trauma is increasingly understood not as something that affects only people who have experienced extraordinary events, but as an issue that can be closely connected to the struggles and difficulties people experience in everyday life. In addition to PTSD, Complex PTSD was officially recognized in 2018 as a diagnosis that captures symptoms associated with chronic trauma. Trauma experienced during important stages of growth and development is often referred to as “developmental trauma.”
One way to understand trauma is as a form of stress-related disorder. In the context of interpersonal relationships, it is also important to consider the effects of psychological abuse and control. At the core of these experiences can be a “loss of self.” In the following sections, we will explore these aspects in greater detail.
Stress disorders—common, everyday phenomena close to all of us
“Trauma” may sound dramatic and distant from one’s everyday life. In simple terms, however, trauma refers to stress disorders. Trauma exists on a spectrum, and mild forms are experienced by virtually everyone in daily life. When the severity reaches a moderate level, it is diagnosed as an “adjustment disorder (stress-related disorder),” and at higher severity as “acute stress disorder,” “PTSD,” “Complex PTSD,” or “dissociative disorders.” At some clinics, as many as 90% of visitors are said to present with stress-related disorders—this is how common they are.
→ Related articles
▶ “What is Adjustment Disorder? Understanding its Causes”
▶ “What are Dissociative Disorders and Dissociative Identity Disorder? Causes Explained”
When an animal—including humans—encounters stress that exceeds the threshold of the stress-response system (meeting certain vulnerability conditions), dysregulation arises in the autonomic nervous system, immune system, and endocrine system. This affects domains such as emotion, arousal, cognition, body, and memory, resulting in diverse symptoms and a sense of “ikizurasa.”
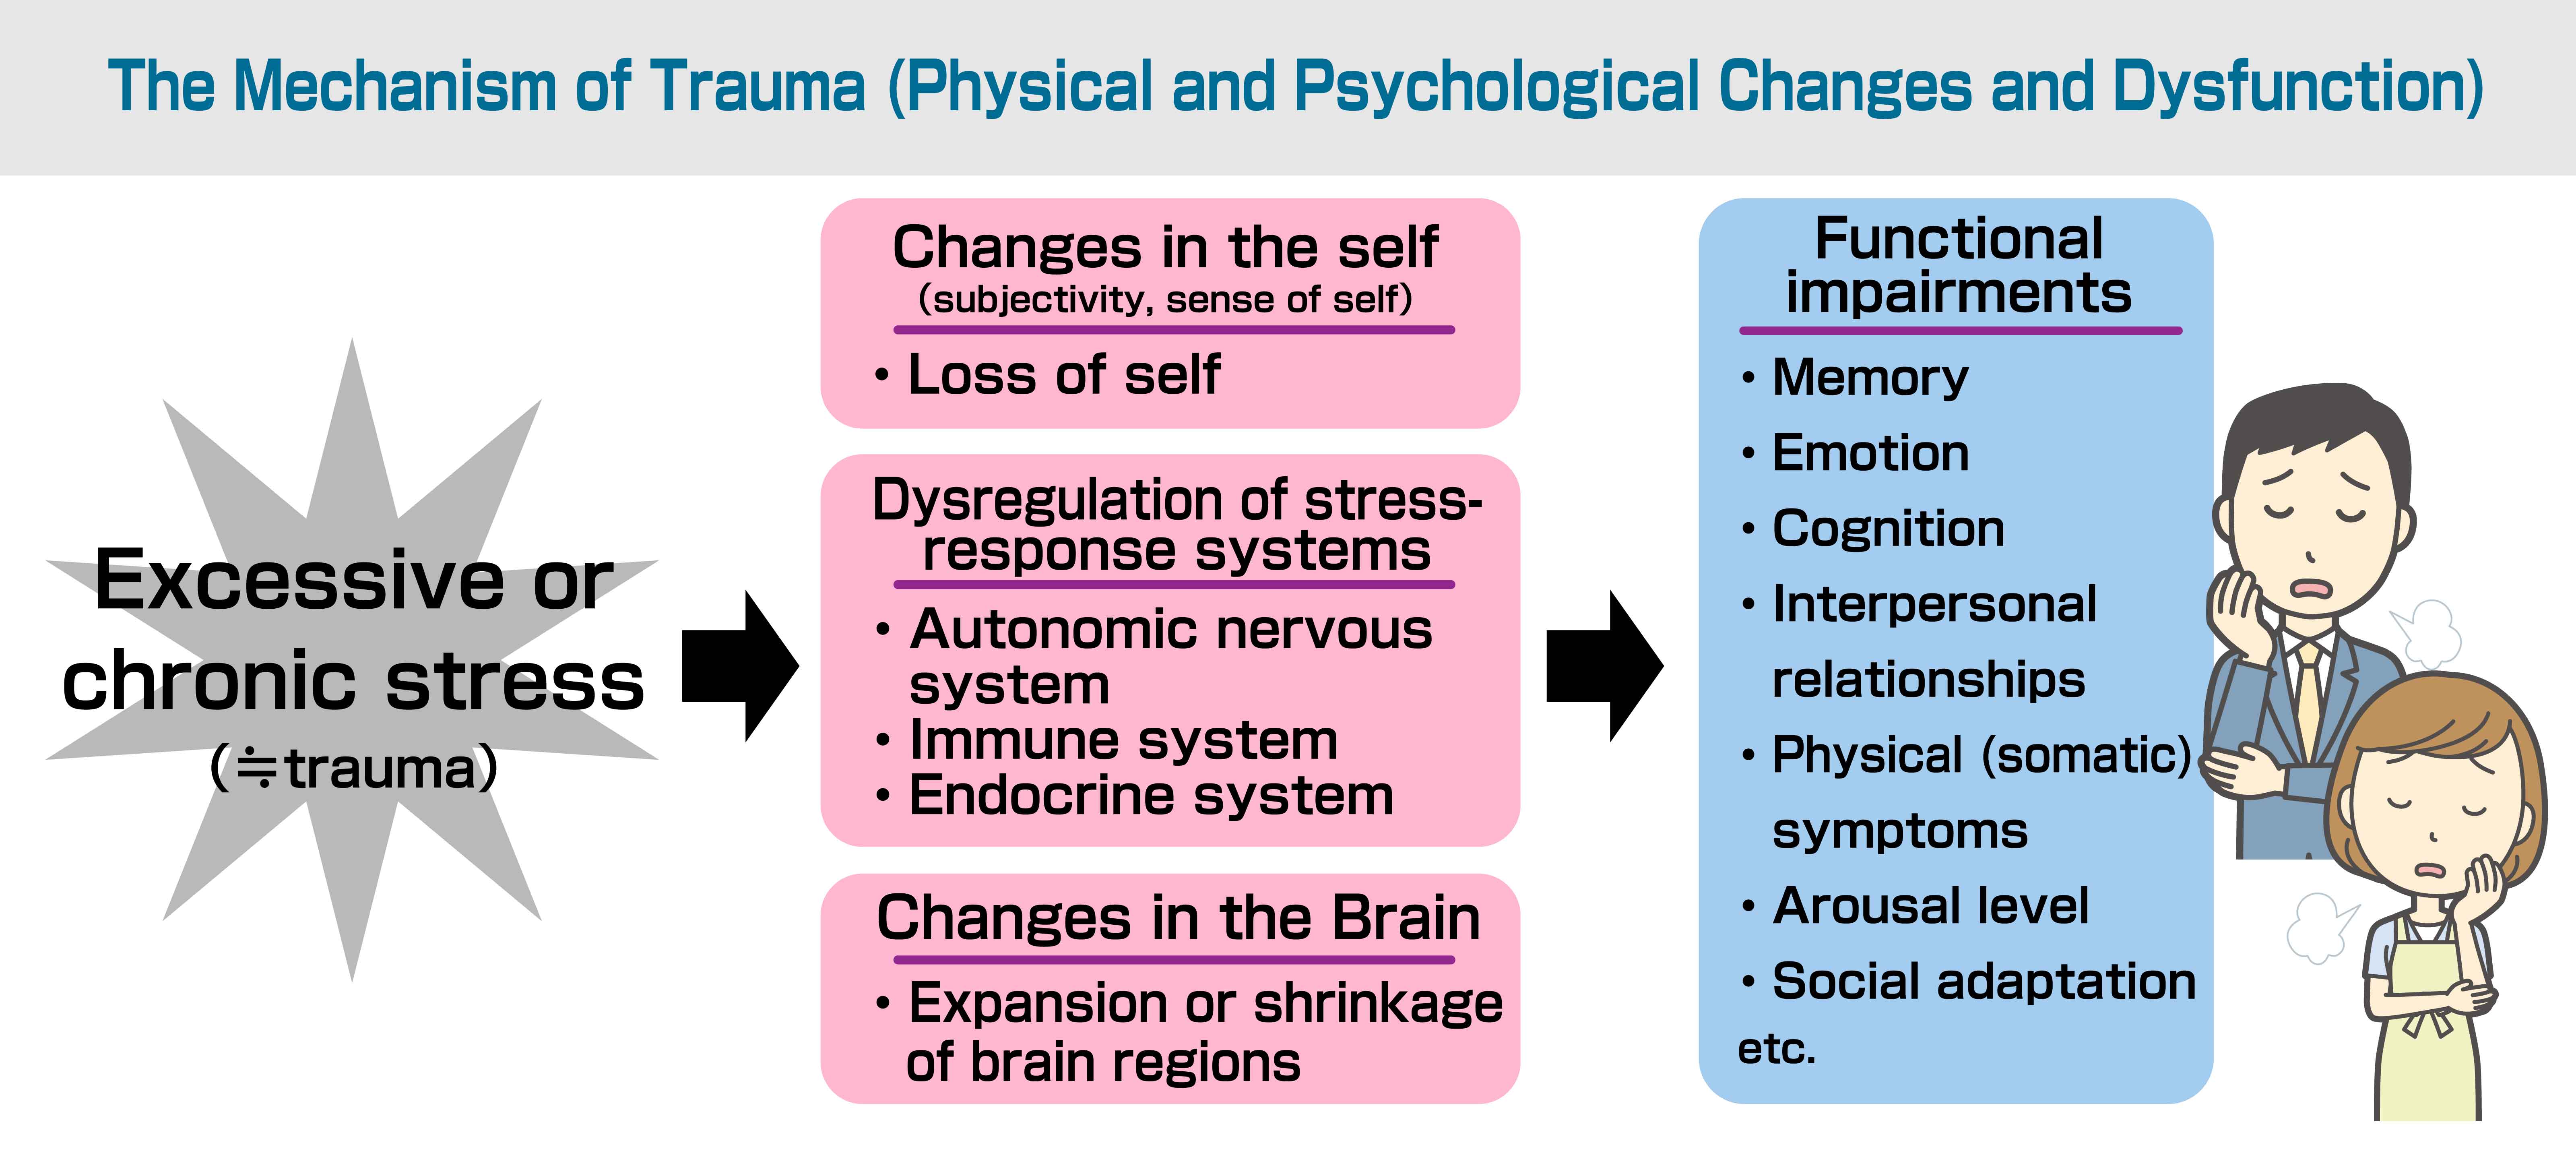
As detailed below, trauma caused by a single, highly intense event such as a disaster or rape is called “single-incident trauma,” while trauma caused by prolonged, gradually accumulating stress is called “complex trauma.”
The human stress-response systems (autonomic, immune, endocrine) are not designed to cope with long-term stress. Therefore, even stress that appears mild on the surface can, when prolonged, cause dysfunction as severe as PTSD.
Another key feature of trauma—Harassment
Alongside stress disorders, another crucial perspective for understanding trauma is to recognize that “trauma is harassment.” In cases where people suffer long after the original events, the influence of harassment is almost always present.
Research on harassment traces back to anthropologist Gregory Bateson’s concept of the “double bind.” A double bind arises when contradictory messages are delivered simultaneously, disrupting a person’s free mental activity.
Bateson identified this as a cause of mental disorders. In everyday life, this includes situations in parent–child, partner, or supervisor–subordinate relationships where someone cloaks self-serving or deficit-driven behavior in plausible reasoning to make the other comply (false rules).
While the body and unconscious sense the other’s unfairness, the conscious mind is forced to accept it due to the seemingly reasonable logic—leading to compliance. Harassment, simply put, is the repetition of this pattern. Victims gradually lose trust in their own perceptions, become isolated from society, and end up controlled by the perpetrator.
Even with single-incident traumas such as accidents, disasters, wars, or rape, those who suffer for a long time almost invariably show the influence of harassment (e.g., social support deficits, secondary harassment). Harassment is a major psychological signature of trauma.
→ Related article
▶What Is Harassment (Moral Harassment)? — Causes and Characteristics
The core of trauma is the “loss of self”—Trauma robs us of being ourselves and creates chronic distress
At the heart of trauma’s impact lies the loss of self—the feeling that one’s self is taken away or has vanished. Trauma deprives us of being ourselves, eroding the fundamental sense that “I am mine.” This is especially pronounced in chronic trauma such as developmental trauma. There are several pathways to this loss: attachment insecurity (unstable relationships with caregivers), taking on family roles in dysfunctional families (e.g., young carers) at the expense of oneself, dysregulation of brain interoception, and interpersonal difficulties that prevent the self from being formed through relationships with others.
“A smartphone that isn’t logged in”
Many trauma survivors are active, resilient people who have survived adversity, so they would never imagine they “lack a self.” Physically they move, but it is as if they’re not logged in with their own ID. The body acts, but the self isn’t there; things don’t truly move by the self or become the self’s experience. As a result, experiences don’t accumulate; nothing feels like it becomes “mine.” This loss of self has been described as “like a display smartphone in an electronics store that isn’t logged in.” In severe trauma, this is strikingly evident. Many trauma-related symptoms can be understood as consequences of self-loss, where the mind and body cannot be properly governed.
Memory dysregulation—“Frozen memories” that stop time
Another lens on trauma is to view it as dysregulation of memory.
Ordinary memories are emotionally weighted by the amygdala, organized by the hippocampus, and stored. But extremely intense stress overactivates the amygdala, overwhelms hippocampal processing, and leaves memories fragmented and lingering out of conscious integration—often called “frozen memories.”
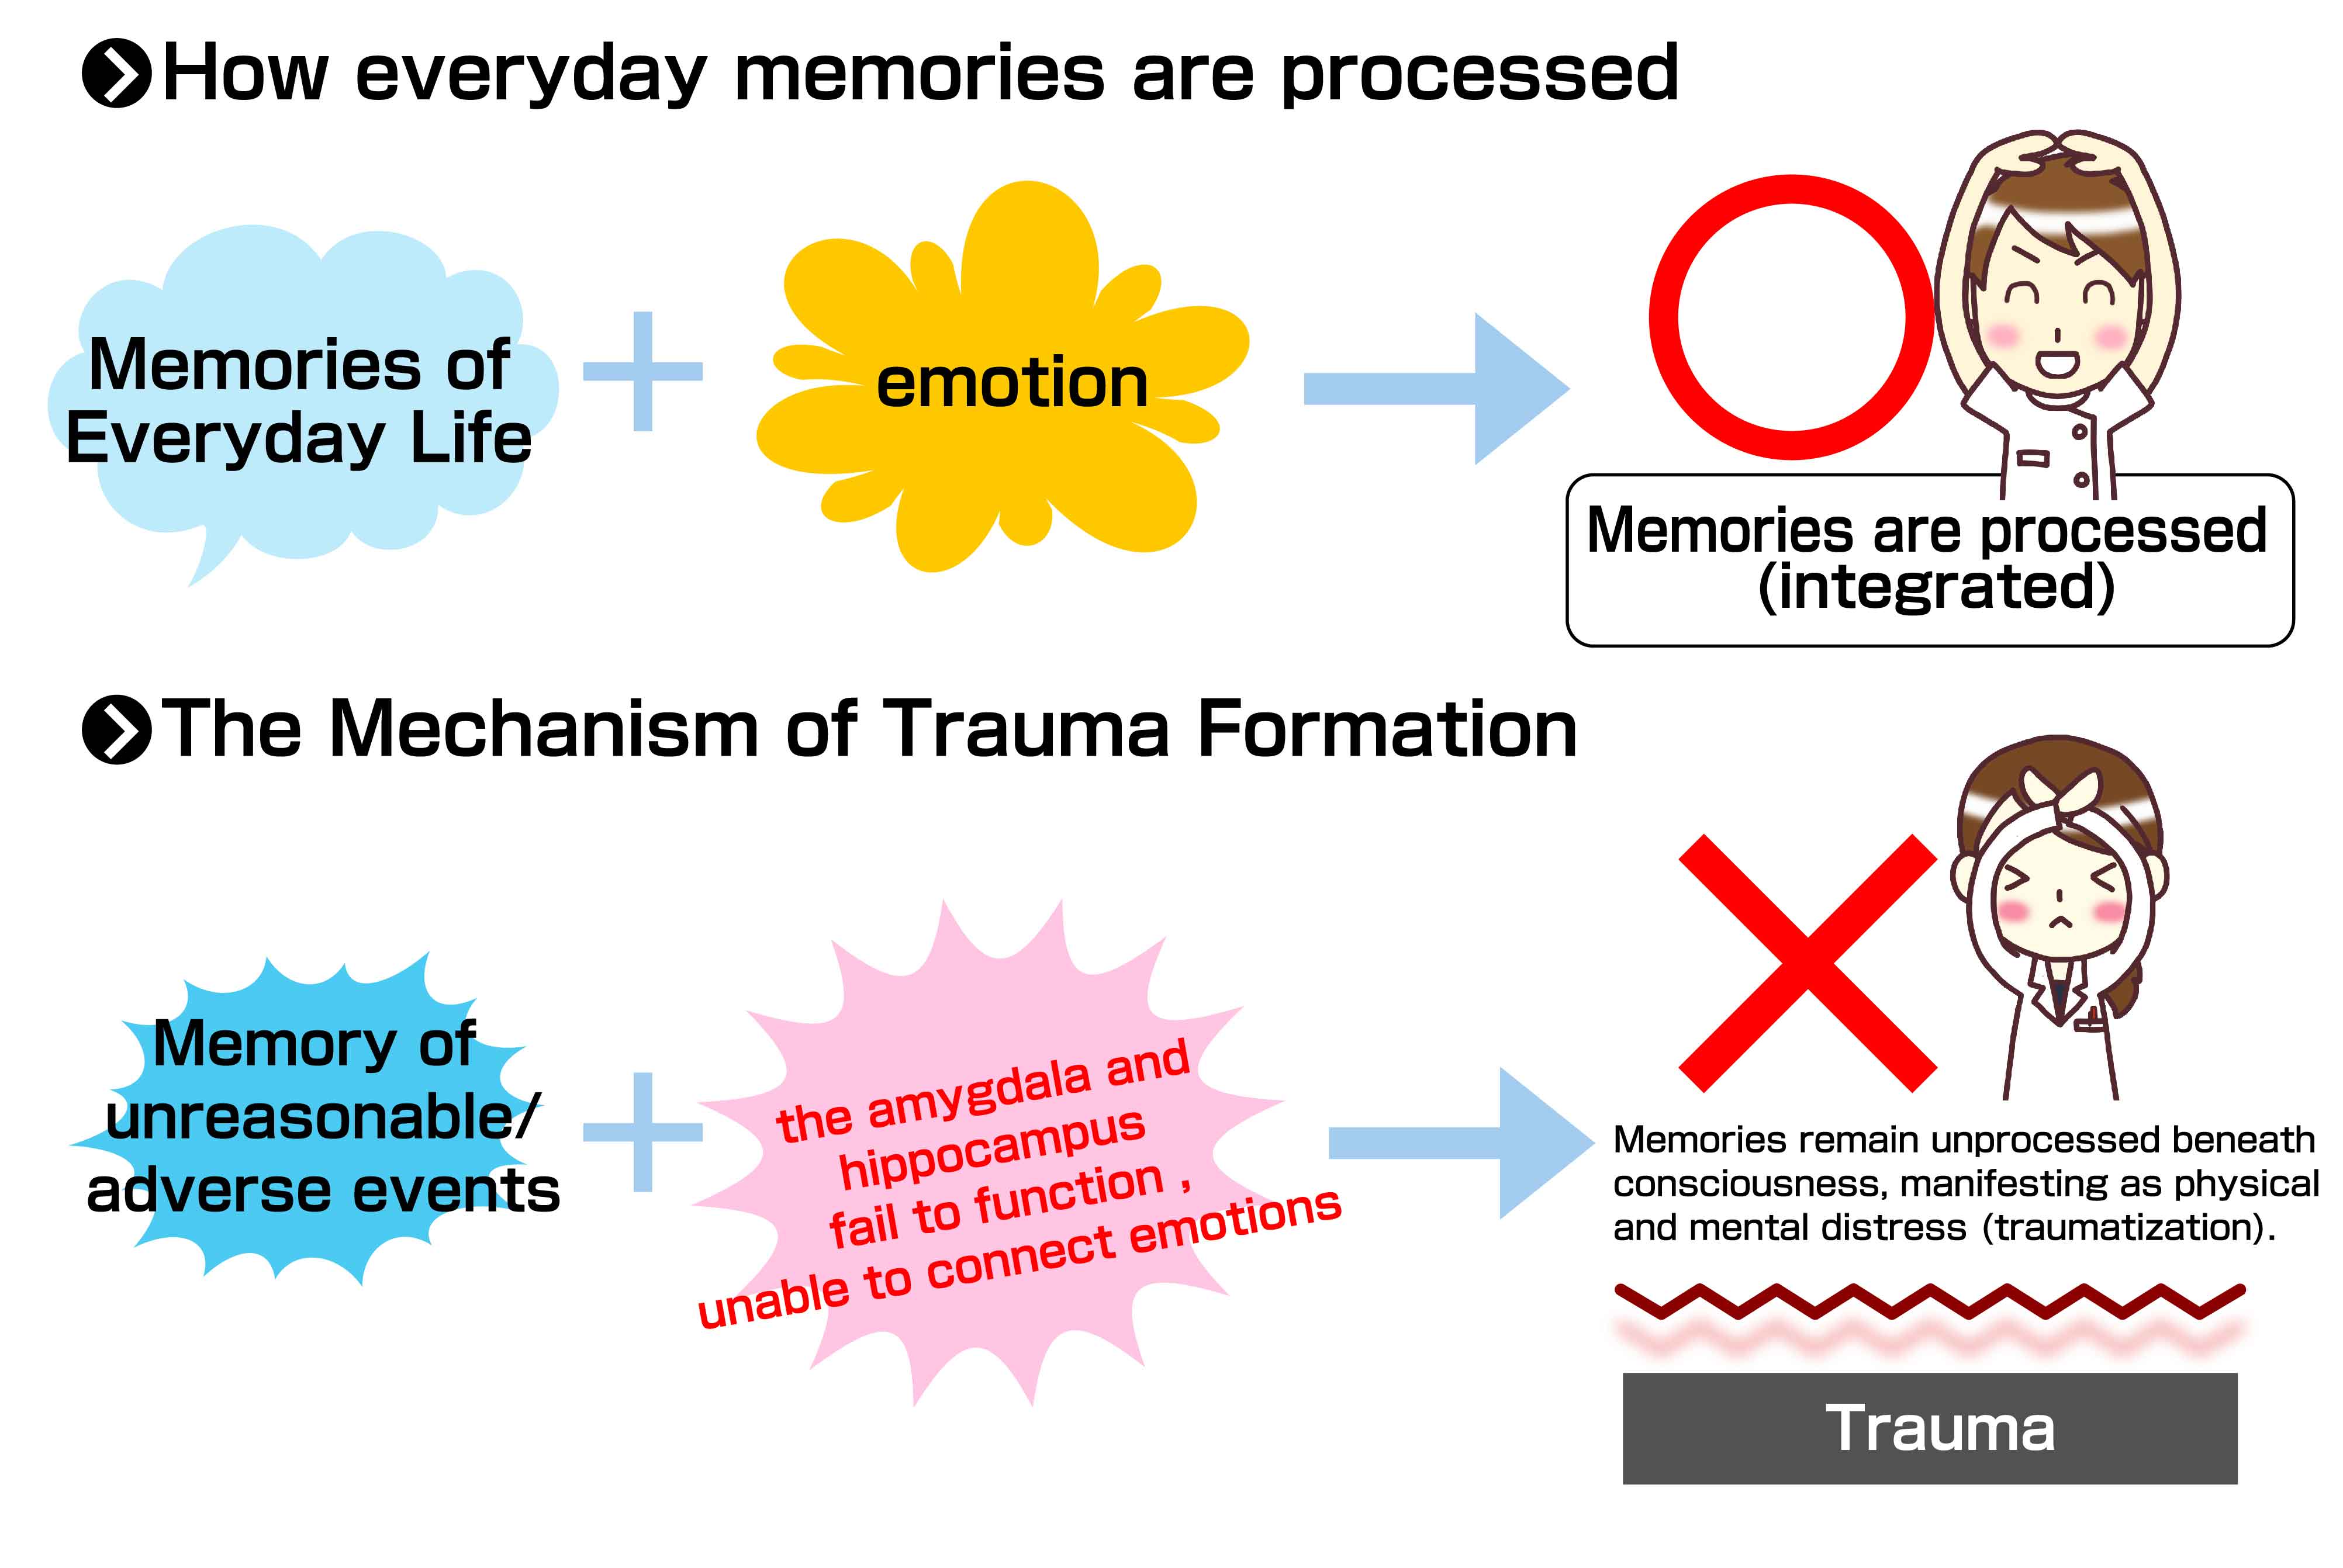
These “unprocessed memories” are thought to drive the phenomenon we call “trauma.” Like a time machine, physical time moves forward, yet the traumatic memory remains fresh; the person lives as if still in the past.
Two broad types of trauma (single-incident / complex)
Trauma can be categorized as:
1) Single-incident trauma: one-off, major stressors such as accidents, disasters, or rape
2) Chronic, repeated trauma (complex trauma): prolonged, repeated stressors such as inadequate caregiving, dysfunctional families, bullying, and harassment*
* Even seemingly minor stresses at home, school, or work can become traumatic when chronic.
Single-incident trauma is obviously serious; however, it is extremely common for people to carry complex trauma without recognizing it. It is no exaggeration to say that most people who seek help for persistent problems carry some form of trauma. Psychiatrist Judith Herman proposed Complex PTSD to describe trauma that cannot be fully explained by the traditional PTSD concept, and in 2018 it was officially adopted into the WHO’s International Classification of Diseases.
Reference: → Judith L. Herman, “Trauma and Recovery” (Misuzu Shobo, Japanese ed.)
What is developmental trauma?
Developmental trauma refers to trauma incurred during the developmental years—primarily in childhood (though the clinically relevant window is handled flexibly). Concrete examples include inadequate caregiving, bullying, and the effects of dysfunctional families.
What is Developmental Trauma Disorder?
Developmental Trauma Disorder is a proposed diagnosis intended to appropriately capture the wide range of symptoms that appear when a child experiences complex, repeated trauma. Arising from developmental-stage trauma, it can present as ADHD-like symptoms, conduct problems, dissociation, etc., and often culminates in Complex PTSD. It has not yet been formally adopted as a diagnostic criterion. While the terms sound similar, “Developmental Trauma Disorder” specifically proposes criteria for children exposed to inadequate caregiving and related adversities.
What Is PTSD / Complex PTSD?
・What Is PTSD?
PTSD generally develops following direct or indirect exposure to a single or relatively short-term traumatic event involving actual or threatened death, serious injury, or sexual violence. It is characterized by three main groups of symptoms: “re-experiencing” (such as flashbacks and nightmares), “avoidance” (avoiding thoughts, feelings, objects, or situations associated with the trauma), and a “sense of current threat” (such as heightened vigilance).
・PTSD criteria
・Exposure—acute or repeated, and sometimes prolonged—to experiences involving extreme threat or fear, in which escape is difficult or impossible.
(Disasters, war, violence, torture, abuse, rape, etc.; not limited to these.)
When the three symptom clusters below persist for several weeks (under APA criteria, PTSD is diagnosed after symptoms persist > 1 month; < 1 month is “Acute Stress Disorder”).
1) Re-experiencing: reliving the traumatic event (flashbacks, nightmares, etc.)
The traumatic event is repeatedly relived. Severity varies widely. Unlike ordinary recall, re-experiencing is intrusive and vividly engages the senses. Rather than being remembered as past, it is felt as if happening now. Experiencing it as happening now is called a “flashback,” while during sleep it appears as “nightmares,” and in thought as “intrusive symptoms.” Children may reenact the trauma in play. *Flashbacks vary in degree and content.
2) Avoidance: avoiding reminders of the traumatic event
People try to avoid situations or individuals that evoke the trauma. Degrees vary—from explicit avoidance to vague reluctance or aversion. Some change jobs, schools, or residences.
3) Sense of current threat
A persistent sense that danger is still present nearby, and that one might be suddenly threatened. Even without conscious awareness, this may appear as chronic over-tension, bodily stiffness, fatigue, over-accommodation to avoid risk (overadaptation), hyperarousal, sleep problems, social/relationship fears, and more.
Reference: Under the APA’s DSM-5-TR (Igaku-Shoin, Japanese ed.), negative alterations in mood and cognition (e.g., persistent negative beliefs) are also included.
What Is Complex PTSD?
Complex PTSD (CPTSD) refers to symptoms associated with prolonged or repeated exposure to chronic trauma. It is diagnosed when, in addition to the three core symptoms of PTSD (“re-experiencing,” “avoidance,” and a “sense of current threat”), three additional types of symptoms are present: “difficulties in emotion regulation,” “negative self-concept” (such as feelings of worthlessness), and “difficulties in relationships.”
Diagnosis, of course, is not based on symptoms alone. A person’s developmental history and recent experiences must also be carefully assessed to establish a history of prolonged or repeated exposure to events of an extremely threatening or horrific nature.
・Complex PTSD criteria
When the above three PTSD clusters (1–3) are present plus the following three, Complex PTSD is diagnosed. *Clinically, some flexibility is applied; the point is that, in addition to the PTSD clusters, the following three are characteristic of Complex PTSD—often summarized as “3 + 3.”
4) Disturbances in emotion regulation
Emotions become overly intense, explosive, or expressed in self-destructive behavior; conversely, emotions may be numbed or dissociated, with diminished access to positive feelings.
5) Persistent negative self-concept
Enduring feelings of worthlessness or insignificance; shame, guilt, defeat.
6) Disturbances in relationships
Difficulties forming relationships; avoiding or devaluing closeness and social engagement; trouble maintaining relationships; sudden surges of shame, fear, or anger that trigger “reset” urges, etc.
Reference: ICD-11
Want to know whether trauma may be affecting you? Try the simple self-check below.
→ “Trauma(Developmental Trauma, complex PTSD) Check for Self-Understanding”
What experiences cause trauma?
・Trauma arises when experiences exceed the threshold of the stress-response system (given certain vulnerability factors)
Traditionally, “traumatic experiences” referred to catastrophes such as train accidents or war, or to rape and abuse. The APA’s DSM-5-TR describes exposure to actual or threatened death, serious injury, or sexual violence (direct experience, witnessing, or learning of it). In reality, even ordinary events can become traumatic when, under certain environmental conditions, they exceed an individual’s stress-response threshold (i.e., vulnerability variables), especially over time.
Stress (event) + Individual sensitivity (resilience) + Environment (vulnerability variables) = Trauma
is a useful way to understand it.
・What counts as a traumatic experience?—Everyday stressors such as marital conflict or dysfunctional families are key causes
What used to be dismissed—like parents’ shouting matches—are now officially recognized as abuse under the label “witnessed domestic violence.” Some studies indicate that the combination of witnessing DV and verbal abuse causes the most severe damage—even more than physical abuse or neglect.
Beyond that, chronic, everyday stressors—dysfunctional families, bullying, harassment, and the absence of appropriate communication—are major causes of trauma. Stress research shows that prolonged stress without foreseeable relief leads to stress disorders; seemingly “small things,” when chronic, can indeed become traumatic.
Trauma is not a single, specific event
In counseling, people sometimes ask, “What is my trauma?”—a common misconception. Trauma is not, by default, a single event. As noted above, it refers to the overall environment and experiences that produce a stress disorder. And difficulties are almost always multi-causal. Clinically, cases attributable to one discrete event alone are actually rare.
Main symptoms caused by trauma
The effects of trauma can appear in many different forms. In addition to symptoms commonly associated with PTSD, such as flashbacks, avoidance, and hyperarousal, they may include chronic tension, excessive adaptation to others, negative self-perception, difficulties in emotion regulation, dissociation, insomnia, physical symptoms, and difficulties in interpersonal relationships.
For more information, please see the page below.
Healing and overcoming trauma
For approaches to healing and overcoming trauma, see the page below:
▶ “Overcoming and Healing Trauma (Developmental Trauma), PTSD, and Complex PTSD”

* If you wish to reprint or otherwise reuse content from this site, please credit the site name as the source or include a link back to this page.
(References / Sources)
Judith L. Herman, “Trauma and Recovery” (Misuzu Shobo, Japanese ed.)
Ichitaro Miki, Developmental Trauma: The Real Cause of “Ikizurasa” (Discover Keisho)
Hiroko Mizushima, “Understanding Psychological Trauma & PTSD” (Gijutsu-Hyoronsha)
Shigeki Mori, “Discovery of Trauma” (Kodansha)
Naoko Miyaji, “Trauma” (Iwanami Bunko)
Nozomu Asukai, “All About PTSD and Trauma” (Kodansha)
Kenichiro Okano, “New Traumatic Disorders” (Iwasaki Academic Press)
Quarterly Be! (Ask Human Care), Sept. 2015
Miyako Shirakawa, “Trauma Care of Little Red Riding Hood and the Wolf” (Ask Human Care)
Akemi Tomoda, “Attachment and Abuse,” in Neuroscience of Brain Development (Shin-yo-sha)
Bessel van der Kolk, “The Body Keeps the Score” (Kinokuniya, Japanese ed.)
Masatoshi Tanaka, “The Neuroscience of Stress” (Kodansha)
Robert M. Sapolsky, “Why Zebras Don’t Get Ulcers” (Japanese ed.)
American Psychiatric Association, DSM-5-TR (Igaku-Shoin, Japanese ed.)
Stephen W. Porges, “The Pocket Guide to the Polyvagal Theory” (Shunjusha, Japanese ed.)
Haruo Sugi, “What is Stress?” (Kodansha)
Donna Jackson Nakazawa, “Childhood Disrupted” (PanRolling, Japanese ed.)
Nadine Burke Harris, “The Deepest Well” (PanRolling, Japanese ed.)
Masashi Kawano, “Trauma-Informed Care” (Seishin-Kango Publishing)
Yuko Nosaka, “Trauma-Informed Care: Reframing ‘Problem Behavior’” (Nihon Hyoronsha)
Journal Psychotherapy, Vol. 45, No. 3: “Clinical Practice of Complex PTSD” (Kongo Shuppan)
etc.










